


Beyond Steroids: Mycophenolate Mofetil Dosing in Immune Checkpoint Inhibitor-Mediated Hepatitis
DOI:
https://doi.org/10.14740/jmc5381Keywords:
Mycophenolate, Immune checkpoint inhibitor-induced hepatitis, CorticosteroidsAbstract
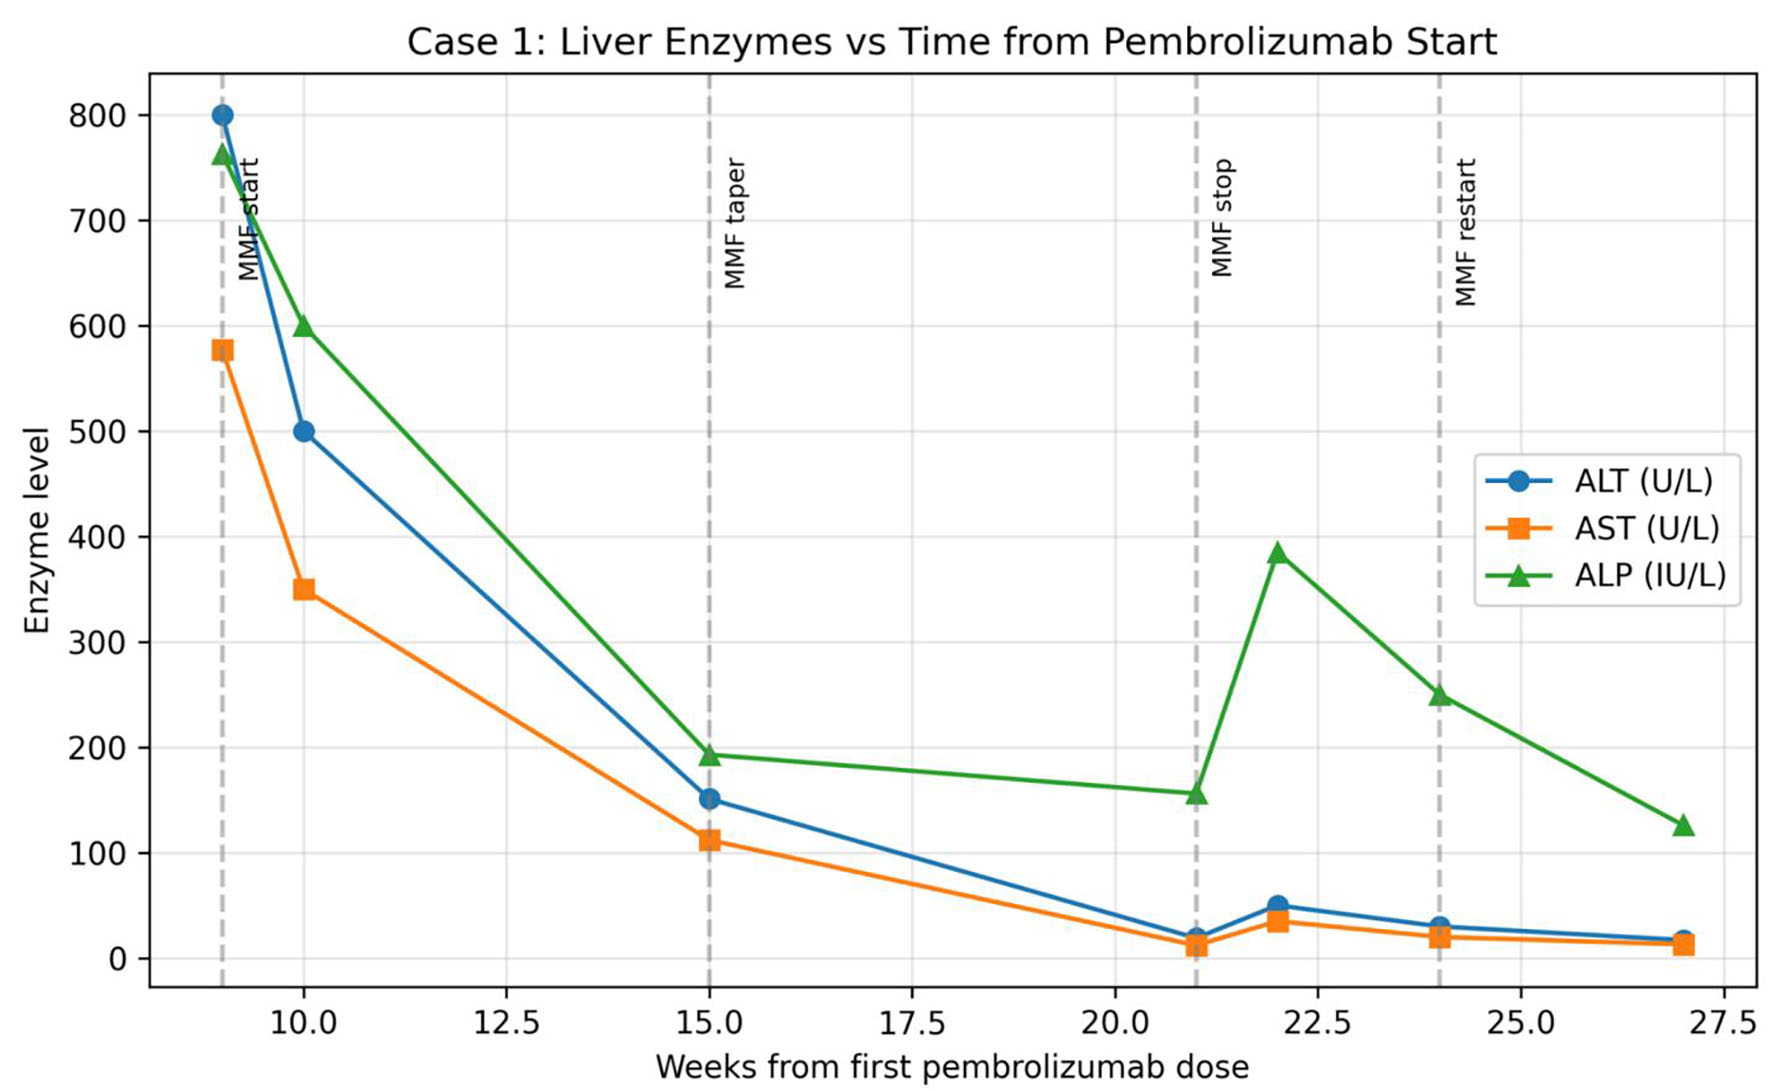
Hepatotoxicity associated with immune checkpoint inhibitors (ICIs) is commonly characterized by elevation of serum aminotransferases, often leading to immunotherapy interruption affecting outcomes in cancer. Low-grade hepatitis usually responds to corticosteroids, but high-grade hepatitis often requires higher doses of steroids or additional immunosuppressants such as mycophenolate mofetil (MMF). With limited literature on MMF dosage and tapering, we present a case series of three patients who developed ICI-mediated hepatitis (ICH), ranging from grade 2 to 4, and were successfully treated with MMF along with concurrent low-dose corticosteroids. In all three cases, alternative etiologies, including viral hepatitis, auto-immune hepatitis, biliary pathologies, and hepatotoxic medications, were ruled out. Corticosteroids were initiated as first-line therapy for all patients; however, when the serological response remained minimal after the first 3 days, MMF was added at a dose ranging from 500 to 1,000 mg twice daily. Liver enzymes demonstrated a measurable decline within the first week of MMF initiation, with complete normalization achieved within 4–12 weeks during which MMF was gradually tapered. Two out of three patients experienced hepatitis relapse, with one following MMF cessation and another upon ICI rechallenge, both of whom responded successfully to MMF re-initiation at lower maintenance doses; two out of three patients had diarrhea, which was managed conservatively and one out of three patients had mild leukopenia, which was observed closely. MMF is a potent alternative for high-dose corticosteroids with a very manageable adverse effect profile and helps us avoid the severe side effects related to steroids, notably hyperglycemia, psychosis, infections, and poor outcomes in patients diagnosed with cancer. In one patient, hepatitis recurred after stopping MMF which was managed with re-initiation of MMF, which suggests that liver enzymes should be monitored on low-dose MMF even after their normalization rather than hastily stopping it. Moving forward, studies with larger sample sizes are needed to establish guidelines regarding MMF dosing and its tapering.
Published
Issue
Section
License
Copyright (c) 2026 The authors

This work is licensed under a Creative Commons Attribution 4.0 International License.








